
Chronic bronchitis - What medications should be used?
Chronic bronchitis is characterized by coughing and sputum production... for at least 3 months each year (possibly intermittent), lasting at least 2 years (but not due to tuberculosis, fungal lung infections, abscesses, or bronchiectasis).
Acute exacerbations can lead to bronchiectasis and bronchial obstruction (known as chronic obstructive bronchitis), resulting in reduced ventilation, alveolar dilation, respiratory insufficiency, and cor pulmonale.
The primary causes of increased bronchial secretion are viruses and bacteria. However, bacteria from infections in the upper respiratory tract, teeth, mouth, and sinuses can cause secondary infections, leading to complications of an acute exacerbation of chronic bronchitis.
Treatment may involve medications to alleviate symptoms and antiviral or antibacterial drugs.
Symptom-relieving medications
Expectorants: Accumulated secretions in the bronchi obstruct the airways. Expectorants facilitate the cough reflex, expelling the secretions and clearing the airways. If the secretions are few but thick and difficult to expel, expectorants such as sodium benzoate or terpinhydrate can be used to thin them. If the secretions are numerous and thick, and thinning them would increase their volume, making ventilation difficult, then sulfur-containing expectorants such as acetylcysteine or carboxycysteine can be used.
These substances act on the gel phase of secretions, breaking the disulfide bonds of glycoproteins, thereby altering the structure and destroying the secretions. Cough suppressants can be used, but only at appropriate doses; high doses should not be used in an attempt to stop coughing immediately, as excessively high doses can suppress the cough reflex, hindering the expulsion of secretions.
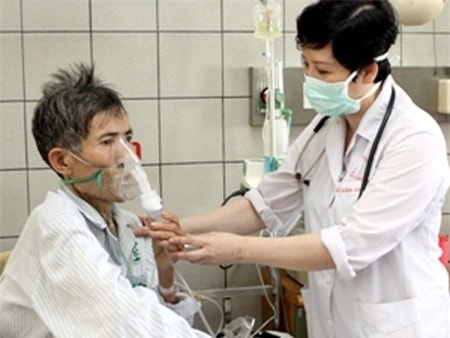 |
| Treatment for patients with bronchitis |
Anti-inflammatory medication: Inflammation hinders airflow. Oral, inhaled, or nebulized corticosteroids are used; in severe cases, injectable forms are used to reduce inflammation. Note: For oral and injectable forms, only use doses sufficient for effectiveness for a short period (no more than 10 days) to avoid systemic side effects (fluid retention, decreased immunity). Inhaled forms rarely cause systemic side effects and can be used for longer periods; however, prolonged use may lead to fungal superinfection, so thorough rinsing of the mouth and throat is necessary after each use.
Bronchodilators: These medications use bronchodilators to reduce airway obstruction, such as theophylline and beta-2 agonists (short-acting types like salbutamol, terbutaline, and fenoterol, and long-acting types like salmeterol and formoterol).
Theophylline has a bronchodilating effect, thus reducing shortness of breath. It also has diuretic and heart-tense effects, and stimulates the nervous system. Using the right therapeutic dose will maximize its main effects, while high doses will cause side effects. The interval between the effective dose and the toxic dose is short; incorrect use can easily lead to poisoning.
For adults, the drug is poorly tolerated, slowly eliminated, and less toxic, requiring only two doses per day. In contrast, for children, the drug is easily tolerated, rapidly eliminated, and more toxic, requiring 4-5 doses per day. Most drugs are metabolized in the liver and excreted in the urine, so they should not be used by people with liver or kidney failure, or young children whose liver's ability to clear toxins is not yet strong enough. The drug is secreted into breast milk and should not be used by breastfeeding mothers; if the mother needs to use it, the child should be given supplemental breast milk.
Beta-2 agonists stimulate beta-2 adrenergic receptors, leading to smooth muscle relaxation, bronchospasm relief, and airway clearance. The appropriate medication is chosen depending on the severity of bronchial obstruction (long or short duration). Inhaled medications via the nose and mouth are used (fast-acting, promptly relieving bronchial obstruction). This group has side effects: increased oxygen demand at rest, resting tachycardia, arrhythmias, tremors, and hypokalemia. Oral medications should be avoided due to slow absorption, delayed onset of action (not promptly relieving bronchial obstruction), higher doses required, and a higher risk of cardiovascular stimulation, agitation, muscle tremors, and headaches.
Both anticholinergics and beta-2 agonists can lead to drug dependence (subsequent courses require higher doses to achieve the same effect). They should not be used for extended periods but rather intermittently.
Antiviral and antibacterial drugs
Antiviral therapy: Antiviral drugs are used to combat the cause of chronic bronchitis. Commonly used medications are antiviral drugs against influenza A.
Antibacterial treatment: Depending on the severity and danger caused by the bacterial strain, common or strong antibiotics may be used, either a single antibiotic or a combination of two or more. Each course of treatment lasts 8-15 days for mild cases and 4-6 weeks for severe cases. Some antibiotics that can be used include: benzylpenicillin, ceftriazone, augmentin, etc.
Chronic bronchitis is quite dangerous, especially during episodes of secondary infection, and requires aggressive treatment. Symptom-relieving medications and antibiotics should only be used under a doctor's specific prescription regarding dosage and duration. Patients should not self-medicate.
AloBacsi.vn


